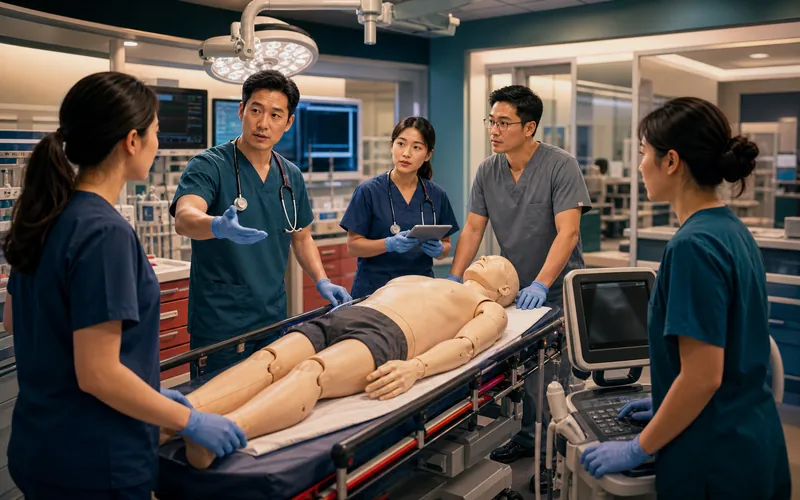
匿名化复合场景:患者尚未到达,院前信息不完整,团队正在准备空间、角色和资源。学习目标是看懂抢救室,而不是抢答诊断。An anonymized composite scene: the patient has not arrived, prehospital information is incomplete, and the team is preparing space, roles, and resources. The learning goal is to read the trauma bay, not guess the diagnosis.
Airway zonehead of bedCirculation zonebedside / monitorScribeshared recordLearnersafe observer
预计学习Estimated learning time · 25 分钟min
学完这门课,你能……After this course, you can…
辨认床头、床旁、记录与通道区域。Identify head-of-bed, bedside, documentation and access zones.
完成包含已知、未知和担心的院前简报。Give a pre-arrival briefing with known facts, unknowns and concerns.
说明自己的角色、报告对象和复评任务。Explain your role, reporting line and reassessment task.
实习:识别与报告;规培:决策时机与监督下关键步骤;青年主治:团队指挥与资源调度。Intern: recognize/report; resident: decision timing and supervised key steps; early attending: team leadership and resources.
核心章节 · 按真实时间线学Core lessons · follow the real timeline
从接到预警到热复盘:抢救室里的 6 个时刻From pre-alert to debrief: six moments in the trauma bay
每个模块都对应一个真实时刻:看什么、站哪里、说什么,并标出所依据的国际指南。Each module is a real moment: what to look at, where to stand, what to say, and the guideline behind it.
−10 min接预警Pre-alert
记录 ATMIST,判断是否启动创伤团队。Record ATMIST; decide on trauma-team activation.
−5 min团队简报Team brief
组长自我介绍、分配角色、说出预案与求助路径。Leader introduces, assigns roles, states the plan and escalation.
−2 min防护与设备PPE & kit
手套、护目镜、防水衣;吸引开机、加温液体、骨盆带、止血带就位。Gloves, eye protection, gown; suction on, warmed fluids, binder and tourniquet ready.
0 min安静交接Hands-off handover
除致命出血外先停手,听完院前交接再过床。Unless exsanguinating, pause and hear the handover before transfer.
0–10 minxABCDE 并行Parallel xABCDE
各岗位同时工作,组长每完成一轮大声总结。Roles work in parallel; the leader summarises aloud after each round.
结束后After热复盘Hot debrief
5 分钟 STOP5:总结、做得好、待改进、行动项。Five-minute STOP5: summary, went well, improve, actions.
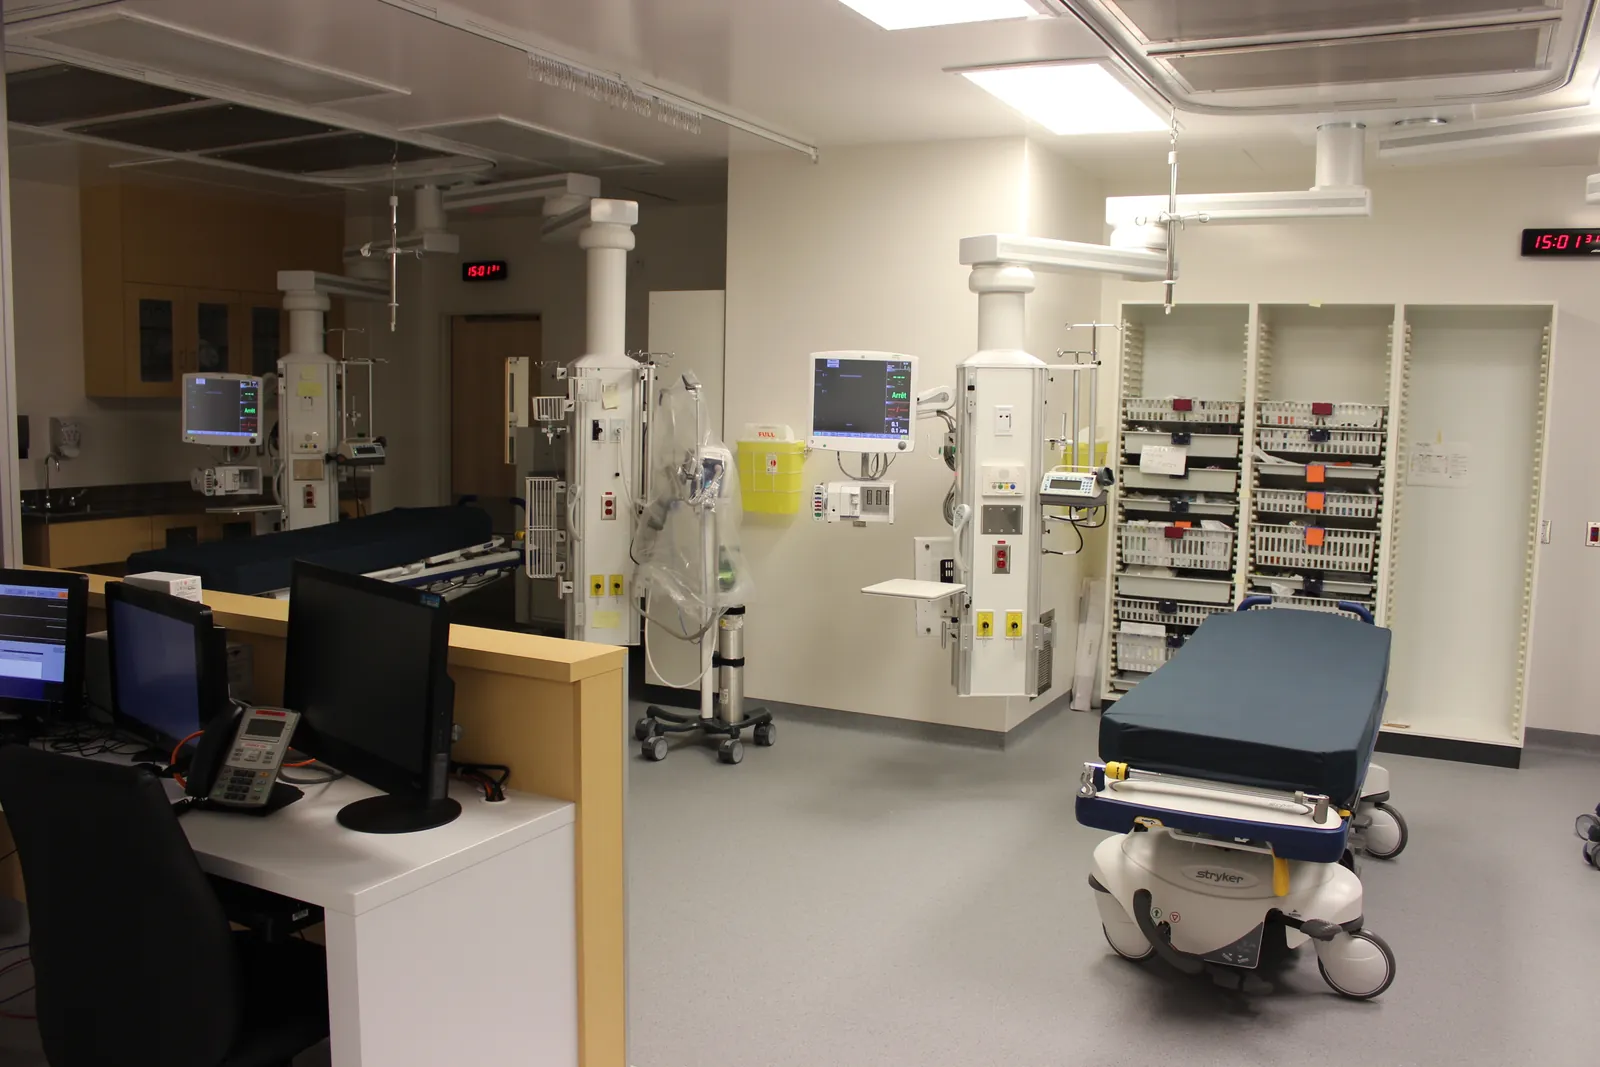
真实照片Real photo蒙特利尔大学医院中心(CHUM)急诊复苏间:床头留给气道,两侧留给操作,床尾留给组长。CHUM resuscitation room, Montréal: head for airway, sides for procedures, foot for the leader.Calvin411 · CC BY-SA 4.0 · Wikimedia Commons
01 · 空间Space
看懂抢救室:每块区域都有固定任务Read the room: every zone has a job
进门先找四样东西:床头气道区、两侧操作区、床尾组长位、通道。站位错了,会挡住别人的生命支持。Find four things first: the airway head, the procedure sides, the leader at the foot, and the access lane. Standing in the wrong place blocks life support.
初学者站记录员旁或床尾一侧,不站床头和两侧操作位。Learners stand by the scribe or at the foot, never at the head or procedure sides.
说什么Say
“我是实习医生 X,可以负责记录/报生命体征。”“I’m intern X; I can scribe or call vital signs.”
ATLS 第 11 版把“复苏团队的功能与沟通”单列为第 2 章,强调到达前准备好环境与团队。ATLS 11 gives team function and communication its own chapter and stresses preparing room and team before arrival.
展开:指南原文要点与教学提示Expand: guideline points and teaching notes
复苏间应预先加温(ATLS 建议患者到达前提高室温并准备加温液体),以减少低体温——低体温、酸中毒与凝血病相互加重。Warm the room before arrival and prepare warmed fluids (ATLS); hypothermia, acidosis and coagulopathy reinforce each other.
真实照片/影像Real image国内 120 救护车(广东东莞)。预警信息从这里开始,决定抢救室准备什么。A 120 ambulance in Dongguan, China. What it reports decides what the bay prepares.廣九直通車 · CC BY-SA 4.0 · Wikimedia Commons
02 · 预警Pre-alert
接预警:用 ATMIST 把一通电话变成准备清单Turn the pre-alert call into a checklist with ATMIST
院前信息不完整是常态。按 ATMIST 记录,在白板上分成“已知 / 未知 / 担心”,并据此决定启动哪个级别的团队。Incomplete information is normal. Record ATMIST, split the board into known / unknown / worried, and choose the team level.
A · TA · T
年龄、性别;受伤时间与预计到达时间(ETA)。Age, sex; time of injury and ETA.
M · IM · I
机制(坠落高度、车速、穿透伤);已发现或怀疑的损伤。Mechanism (fall height, speed, penetration); injuries found or suspected.
S · TS · T
生命体征及变化;已做处置(止血带时间、液体、药物)。Signs and trends; treatment given (tourniquet time, fluids, drugs).
交接格式要固定、简短、按顺序说完;接收方复述关键数字确认。Use a fixed, brief, ordered format; the receiver reads back key numbers.
ATMIST (UK NHS/JRCALC handover) · NICE NG39 Major trauma: service delivery (2016)
展开:指南原文要点与教学提示Expand: guideline points and teaching notes
启动标准各院不同。可参考 ACS COT 2021 现场分诊指南的“红色标准”(如成人收缩压 <90 mmHg、呼吸 <10 或 >29 次/分、不能听从指令、近端肢体离断、怀疑骨盆骨折、需止血带或填塞的活动性出血)作为高级别团队启动的讨论起点。Activation criteria vary. ACS COT 2021 field-triage red criteria (e.g. adult SBP <90 mmHg, RR <10 or >29, unable to follow commands, proximal amputation, suspected pelvic fracture, bleeding needing tourniquet or packing) are a reasonable starting point.
AI 教学插图AI teaching illustration团队在患者到达前完成简报,角色写在白板上。The team briefs before arrival; roles are on the whiteboard.
03 · 简报Briefing
到达前 5 分钟:团队简报和个人防护Five minutes before arrival: brief and protect
组长站到床尾,自我介绍,逐个点名分配角色,说出“如果……就……”的预案,并确认每个人戴好防护。The leader stands at the foot, introduces themself, assigns each role by name, states “if… then…” plans and checks PPE.
ATLS 要求所有接触患者的人员采取标准预防;简报的价值在于让每个人在患者进门前就知道自己的任务。ATLS requires standard precautions for everyone in contact; briefing means everyone knows their task before the doors open.
ATLS 11 · TeamSTEPPS 3.0 (AHRQ, 2023)
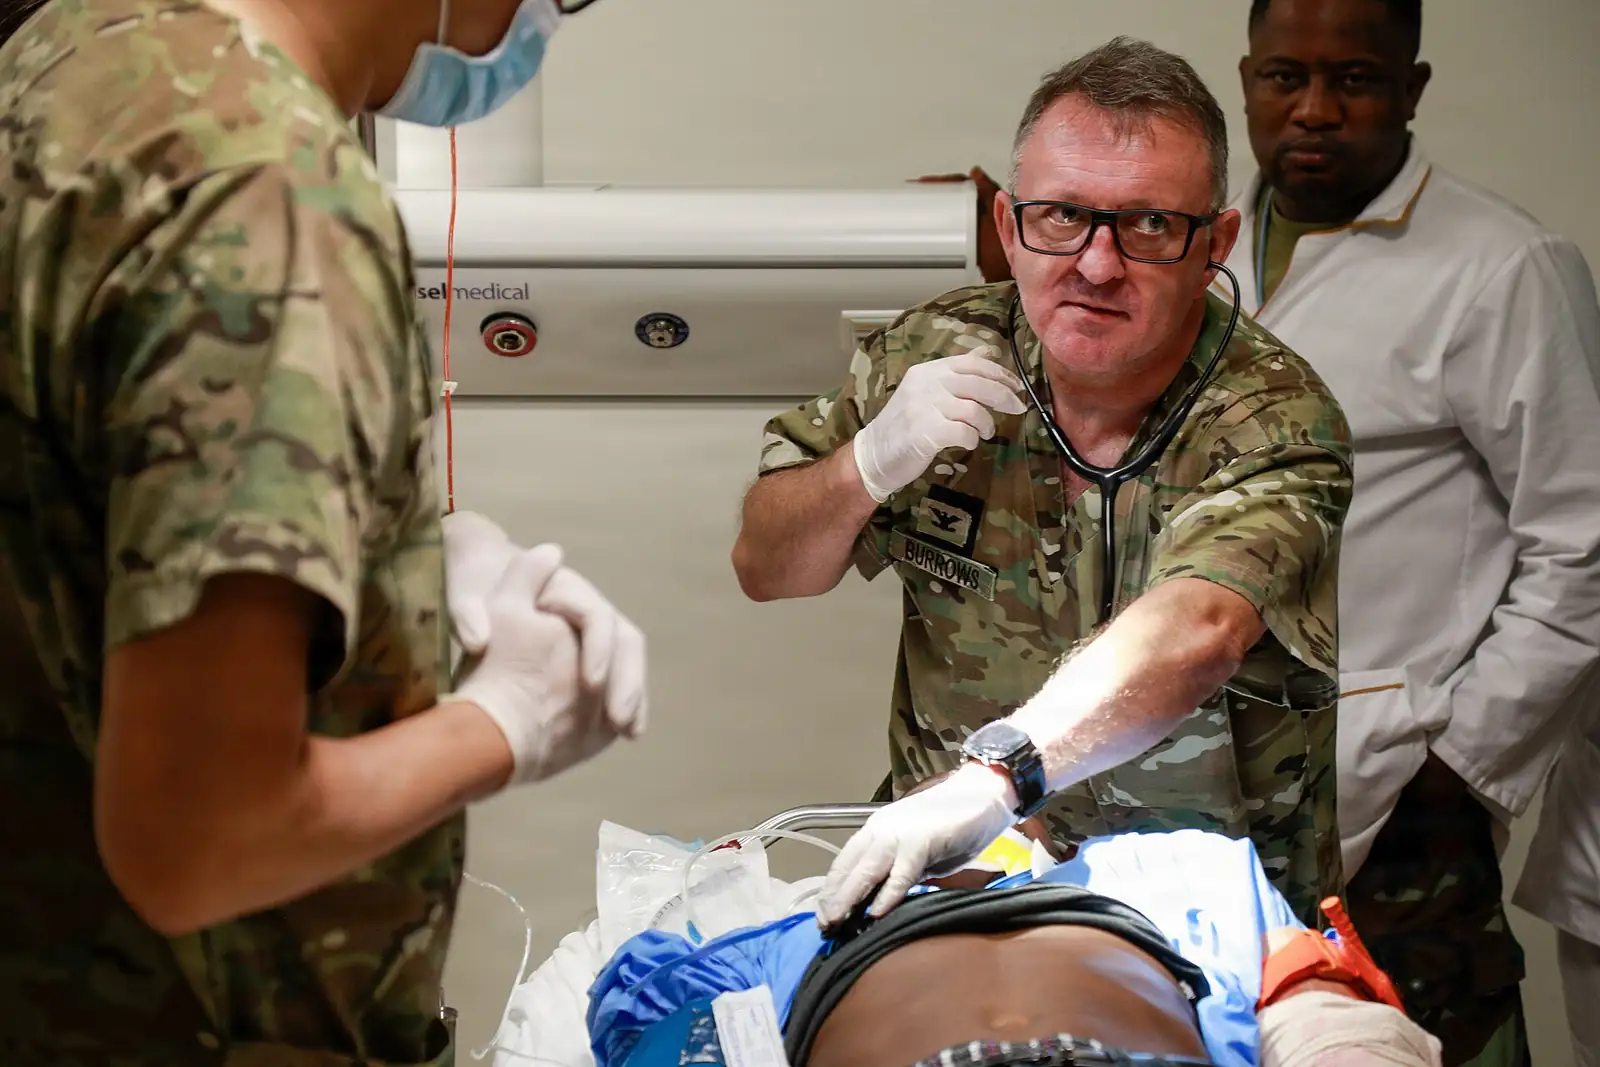
真实照片/影像Real image创伤启动演练:麻醉医生在床旁评估,其他成员各守其位(演练,非真实患者)。Trauma activation drill: an anaesthetist assesses while others hold their positions (simulation, no real patient).U.S. Army photo by Capt. Jordan Beagle · Public domain · Wikimedia Commons
04 · 到达Arrival
0–2 分钟:先听交接,再过床,然后 xABCDE 并行Minutes 0–2: listen, transfer, then parallel xABCDE
患者进门后,除非有致命外出血需要立刻压迫,全队先停手约半分钟听完交接;过床时保持脊柱活动限制(SMR),然后各岗位同时开始。On arrival, unless exsanguinating bleeding needs immediate pressure, the team pauses briefly for handover; transfer with spinal motion restriction, then all roles start together.
气道医生管 A,操作医生管 B/C,护士建通路采血,组长按顺序收集报告。Airway doctor on A, procedure doctors on B/C, nurses on access and bloods; the leader collects reports in order.
复评Reassess
每次干预后、病情变化或转运前,回到 x 重新走一遍。After each intervention, any change, or before transfer, go back to x.
ATLS 第 11 版(2025):初评由 ABCDE 改为 xABCDE,致命性外出血控制先于气道处理。ATLS 11th ed. (2025): ABCDE became xABCDE; control exsanguinating haemorrhage before airway.
ACS ATLS 11 (2025) · European guideline on bleeding, 6th ed. (2023), R2
展开:指南原文要点与教学提示Expand: guideline points and teaching notes
欧洲大出血与凝血病管理指南(2023)推荐:开放伤口局部压迫控制致命出血(1B),手术前可辅助使用止血带控制肢体致命出血(1B)。The 2023 European bleeding guideline recommends local compression of open wounds (1B) and adjunct tourniquets for life-threatening extremity bleeding before surgery (1B).
真实照片/影像Real image院前与院内团队交接病人(演练)。交接时一个人说,其他人听。Pre-hospital to hospital handover (simulation): one speaks, the rest listen.U.S. Army photo by Capt. Jordan Beagle · Public domain · Wikimedia Commons
抢救室最常见的错误不是不会做,而是没人听见、做了两遍或没人做。每条指令点名一个人,对方复述,执行后报告。The commonest failure is not skill but communication: unheard, duplicated or undone. Name one person, they read back, then report completion.
发出Send
“李护士,给 1 g 氨甲环酸,10 分钟静推完。”“Nurse Li, give 1 g tranexamic acid over 10 minutes.”
复述Read back
“氨甲环酸 1 g,10 分钟,明白。”“Tranexamic acid 1 g over 10 minutes, understood.”
关闭Close
“氨甲环酸 1 g 已开始,09:12。”记录员写入时间。“TXA 1 g started at 09:12.” The scribe logs the time.
任何人发现风险都可以叫停:用 CUS——“我担心(Concerned)……我不安(Uncomfortable)……这是安全问题(Safety)”。Anyone can stop the line with CUS: “I’m Concerned… Uncomfortable… this is a Safety issue.”
TeamSTEPPS 3.0 (AHRQ, 2023) · ATLS 11 Ch. 2
展开:指南原文要点与教学提示Expand: guideline points and teaching notes
组长在每轮 xABCDE 后用 10 秒做“小结”:目前发现、当前担心、下一步、谁负责——让所有人重新对齐。After each xABCDE round the leader takes ten seconds to summarise: findings, concerns, next steps, owners.
真实照片/影像Real image深圳市第二人民医院急诊科。国内急诊同样可以在每次抢救后做短复盘。Emergency department, Shenzhen Second People’s Hospital: short debriefs work here too.李汉宗(Lhzss8) · CC BY-SA 4.0 · Wikimedia Commons
06 · 复盘Debrief
结束后 5 分钟:用 STOP5 做热复盘Five minutes after: a STOP5 hot debrief
病人离开抢救室后,团队用 5 分钟复盘,把经验留下来,而不是只留下疲惫。When the patient leaves, take five minutes so the team keeps the lessons, not just the fatigue.
S · TS · T
Summarise 总结病例;Things that went well 做得好的。Summarise the case; Things that went well.
O · PO · P
Opportunities to improve 可改进点;Points to action 具体行动与负责人。Opportunities to improve; Points to action with owners.
55
控制在 5 分钟,对事不对人。Keep it to five minutes; discuss systems, not blame.
STOP5 是急诊科热复盘工具:总结、做得好、待改进、行动项,约 5 分钟完成。STOP5 is an ED hot-debrief tool: summary, positives, improvements, actions, in about five minutes.
Walker CA et al. STOP5. Clin Exp Emerg Med 2020 · TeamSTEPPS 3.0
初学者最常见的 4 个错误Four common beginner mistakes
✕三个人同时围在床头处理气道,没人建通路。Three people crowd the airway; nobody gets access.
✓组长按岗位分工:一人管气道,其他人回到 B/C 和记录位。The leader assigns roles: one on airway, others back to B/C and scribing.
ATLS 11 Ch. 2
✕患者进门就开始剪衣服、抽血,交接没人听完。Cutting clothes and drawing blood while no one hears the handover.
✓除致命出血外,先安静听完 ATMIST,再过床开始操作。Unless exsanguinating, hear ATMIST first, then transfer and start.
ATMIST · NICE NG39
✕口头医嘱只回答“好的”。Answering a verbal order with just “OK”.
✓复述药名、剂量、途径,执行后报告时间。Read back drug, dose and route; report the time when given.
TeamSTEPPS 3.0
✕反复做骨盆挤压试验“确认”骨折。Repeated pelvic springing to “confirm” a fracture.
✓怀疑骨盆骨折时不做挤压分离试验,直接上骨盆带并拍片/超声。If pelvic fracture is suspected, skip springing; apply a binder and image.
教学用途。图中演练与插图均不含真实患者信息;具体启动标准、剂量与流程以最新指南和本院规定为准。For teaching. Drills and illustrations contain no real patient data; follow current guidelines and local protocols.
REAL SOURCES · READ → REASON → REASSESS
看真实空间,练到院前准备Read a real room and practise arrival preparation
照片帮助提出问题:设备在哪里、角色由谁负责、信息怎样闭环。Use the photos to ask where equipment is, who owns each role and how communication closes the loop.
CHUM 复苏间实景CHUM resuscitation room
先看哪里Where to look
先辨认床位、监护与设备通道,讨论哪些准备要在患者到达前确认。Identify the bed, monitoring and access routes; discuss what should be checked before arrival.
这张图不能回答What this image cannot answer
一所医院的布局不代表通用编制、人员站位或操作规范。One hospital layout does not establish universal staffing, positions or procedures.
Wikimedia Commons 文件:Resuscitation room of the CHUM ER level.(无图号;原文件名 CHUM Emergency Level Resuscitation.jpg) · Wikimedia Commons 文件:Resuscitation room of the CHUM ER level.(无图号;原文件名 CHUM Emergency Level Resuscitation.jpg)
保留原图;网页仅按比例显示。读图释义由课程另写,不是原作者诊疗结论。Original image retained and displayed proportionally. Teaching interpretation is separate from the original clinical conclusions.
真实演习:到院前角色简报Real exercise: team role briefing
先看哪里Where to look
观察团队面对面的交流方式,再演练“谁负责、谁复述、何时更新”。Observe face-to-face communication, then practise who owns the task, who repeats it and when to update.
这张图不能回答What this image cannot answer
公开军事演习照片,不是真实患者;照片不能证明标准话术或任务已执行。A public military exercise, not a real patient. The photo does not establish standard wording or completed tasks.
原始图注与许可Original caption and licence
U.S. Army photo by Capt. Jordan Beagle · 公有领域(美国联邦政府作品 PD-USGov-Military-Army) · Original source / 原图出处
Angolan Lt. Cmdr. Joaquim Quibuco, a navy surgeon, briefs his team on roles and responsibilities in preparation for a simulated scenario during the Angola Medical Readiness Exercise at Hospital Militar Principal, Luanda, Angola, Sept. 7, 2026.
保留原图;网页仅按比例显示。读图释义由课程另写,不是原作者诊疗结论。Original image retained and displayed proportionally. Teaching interpretation is separate from the original clinical conclusions.
01
准备不是设备清单Preparation is more than equipment
到院前确认空间可达、监护可用、团队角色与求助路径;具体编制按本地流程。Before arrival confirm access, monitoring readiness, team roles and escalation paths; staffing follows local workflows.
02
交接分清事实与担心Separate facts from concerns
报告机制、已知生理变化、已做事项和未知信息,不把猜测写成观察事实。Report mechanism, known physiologic changes, completed actions and unknowns; do not turn assumptions into observations.
03
核查不延误急救Checks should not delay urgent care
核查帮助团队发现遗漏;立即威胁仍按优先级并行处理,交接后有人持续复评。Checks help identify omissions. Immediate threats remain prioritised and coordinated, with an assigned reassessment owner after handoff.
真实公开图用于观察训练;病例与指南各自标明来源,病例报告不能单独建立普遍治疗规则。Public images support observation training. Case reports and guidelines are distinguished; a case report alone cannot establish a general treatment rule. Clinical applicability remains pending teacher review.
互动题Interactions
抢救室站位判断Trauma bay positioning
选择不阻挡气道、通道、药械和核心任务的位置。Choose a position that does not block airway access, traffic, equipment, or core tasks.
已知/未知分类Known / unknown sorting
把院前通报内容分到已知、未知、需要确认、可能需要资源四类。Sort pre-arrival information into known, unknown, needs confirmation, and may require resources.
沟通语言选择Communication wording choice
选择更适合团队复述确认的短句,不要求给治疗方案。Choose wording suited for team read-back; no treatment plan is requested.
来源与审核状态Sources and Review Status
抢救室团队准备和角色分工用于流程教育,本地确认仍需要。Trauma bay team preparation and role mapping are used for process education; local confirmation is still required.
交接与闭环沟通表述待创伤团队教学审核。Handoff and closed-loop communication wording awaits trauma-team teaching review.